How IIGLP-1 Agonists Work: A Simple Guide
When you see headlines about “IIGLP-1 agonist how it works,” the science can feel a little intimidating. In reality, the concept boils down to a protein that helps regulate blood sugar and appetite, and a drug designed to boost its activity. This article unpacks the biology, the pharmacology, and what early studies suggest about the future of these compounds.
What Is IIGLP-1?
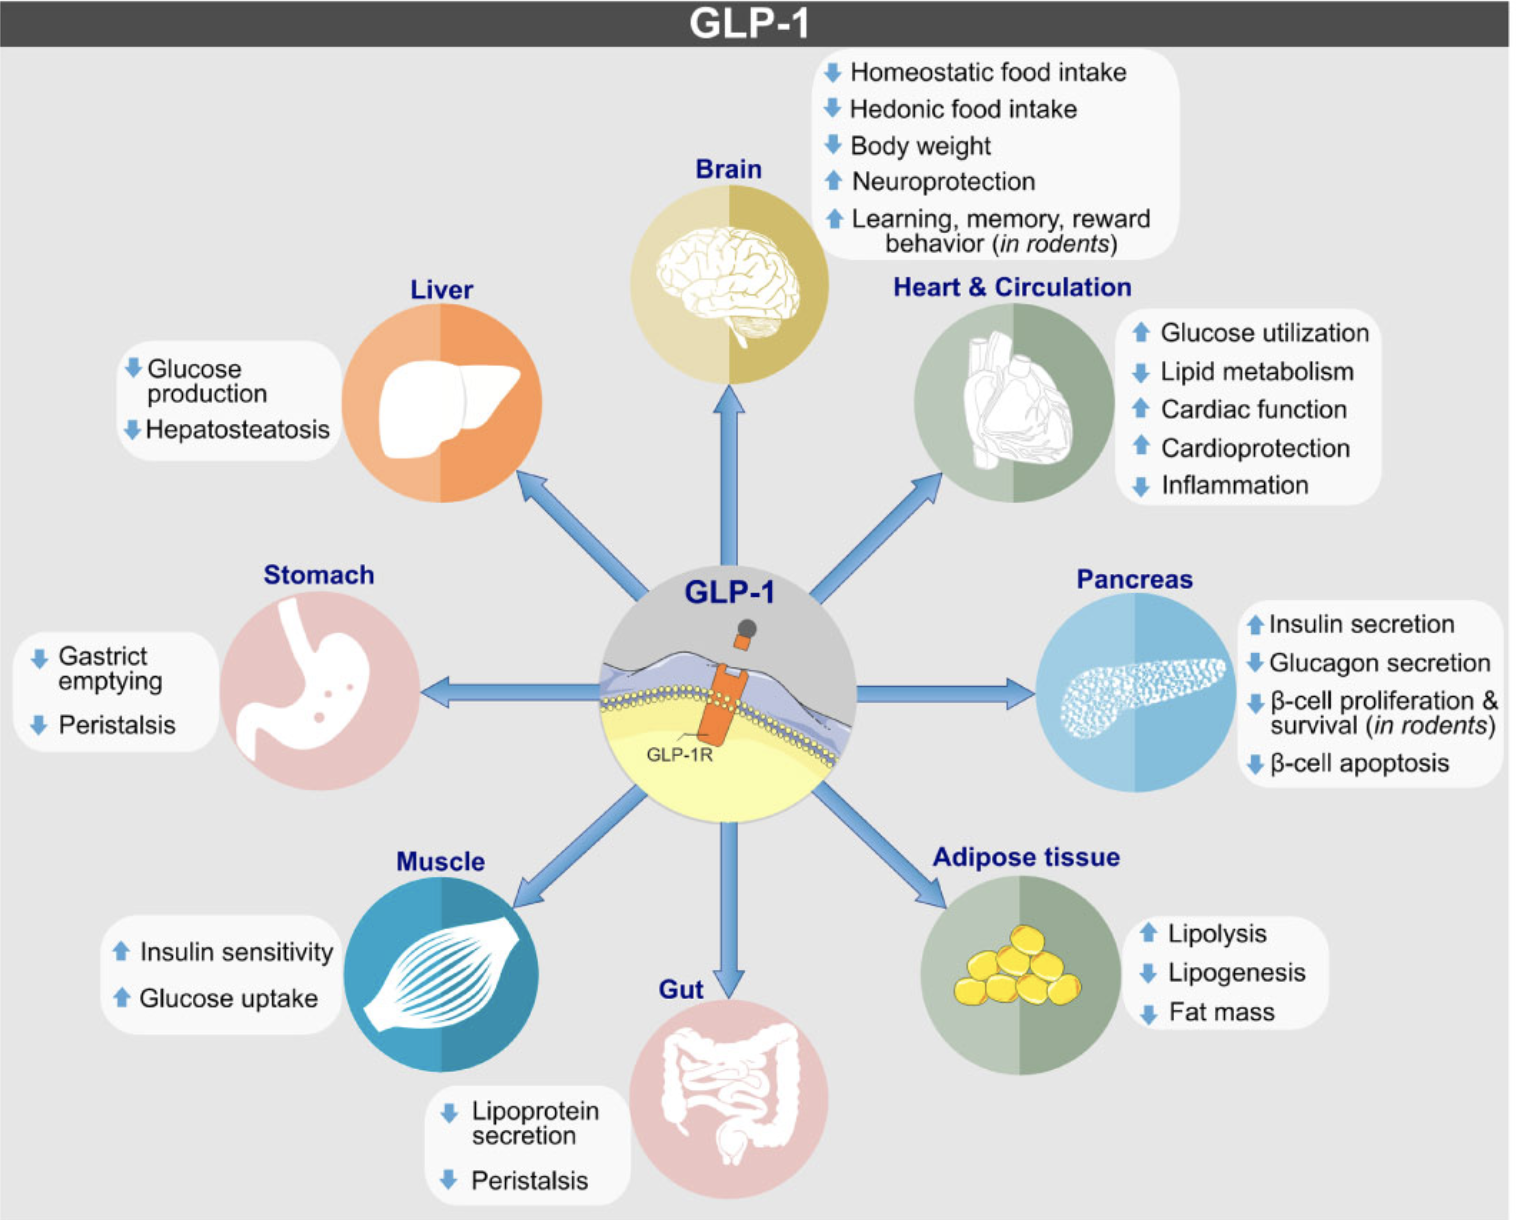
IIGLP-1 (often written as IIGLP‑1 or glucose‑dependent insulinotropic polypeptide) is a hormone released by the small intestine after you eat. It belongs to the incretin family, a group of gut‑derived peptides that tell the pancreas to secrete insulin in response to rising glucose levels. Beyond insulin, IIGLP‑1 also slows gastric emptying, promotes satiety, and influences lipid metabolism.
Unlike its more famous cousin GLP‑1, which has been the basis for several diabetes drugs, IIGLP‑1 has historically received less attention. Researchers now suspect that tapping into its pathway could offer complementary benefits—especially for patients who don’t respond fully to GLP‑1‑based therapies.
Why Target IIGLP-1?
Two main reasons drive the search for an IIGLP‑1 agonist:
- Metabolic synergy: Combining IIGLP‑1 activation with GLP‑1 stimulation may improve blood‑sugar control more than either hormone alone.
- Weight management: Early animal work hints that IIGLP‑1 can reduce food intake by enhancing feelings of fullness.
In practice, a drug that mimics IIGLP‑1 could help patients with type 2 diabetes, obesity, or even non‑alcoholic fatty liver disease—a cluster of conditions often linked to insulin resistance.
Mechanism of Action: How an IIGLP-1 Agonist Works
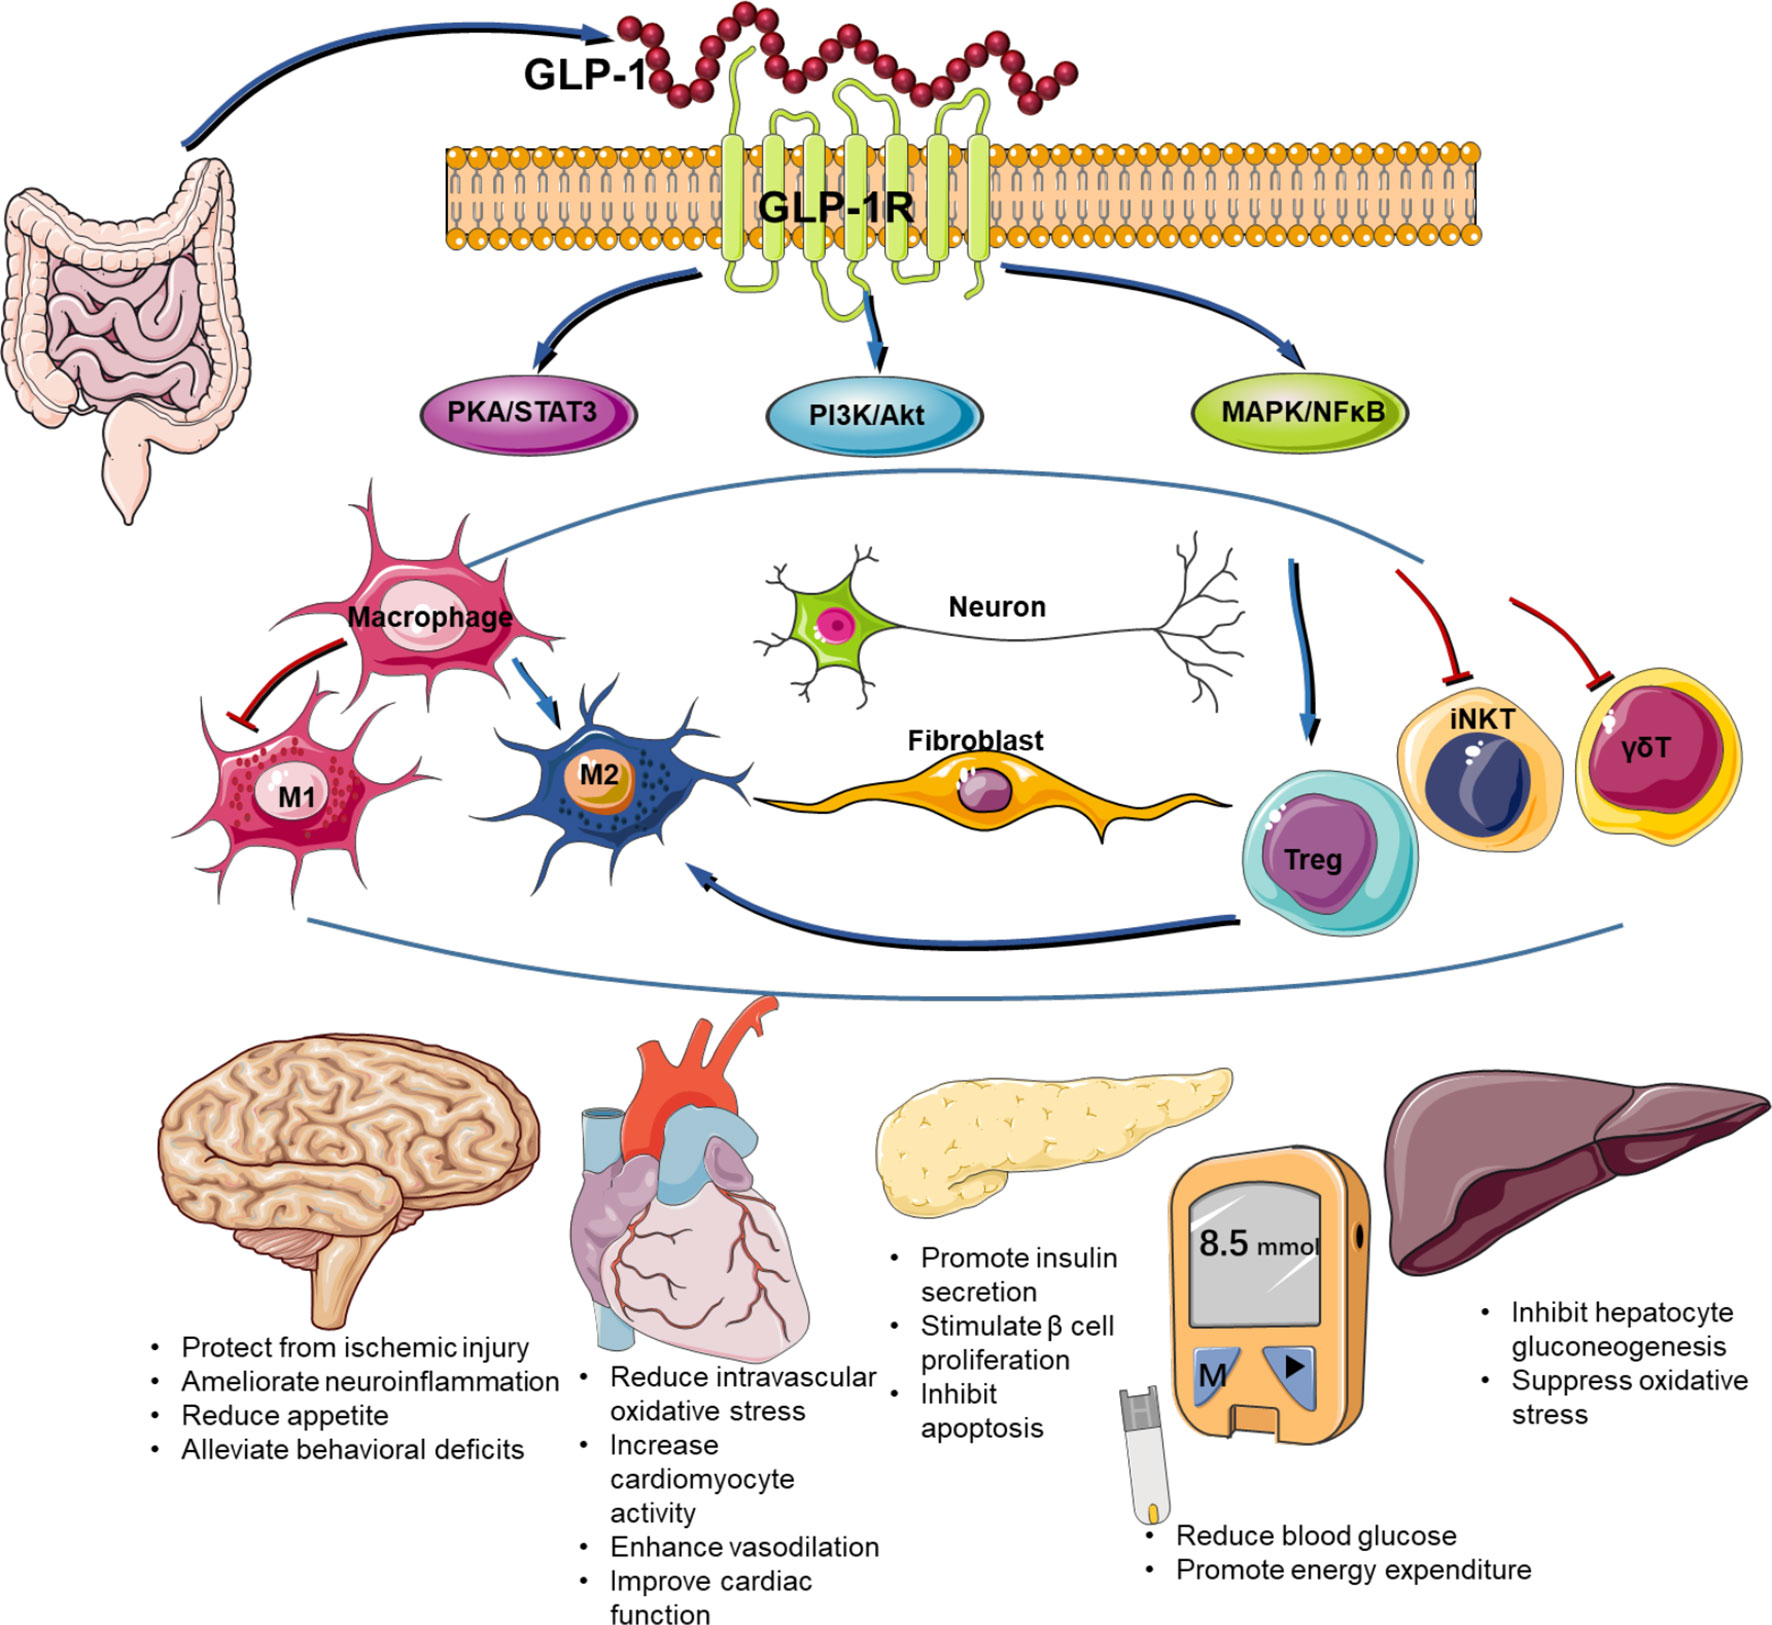
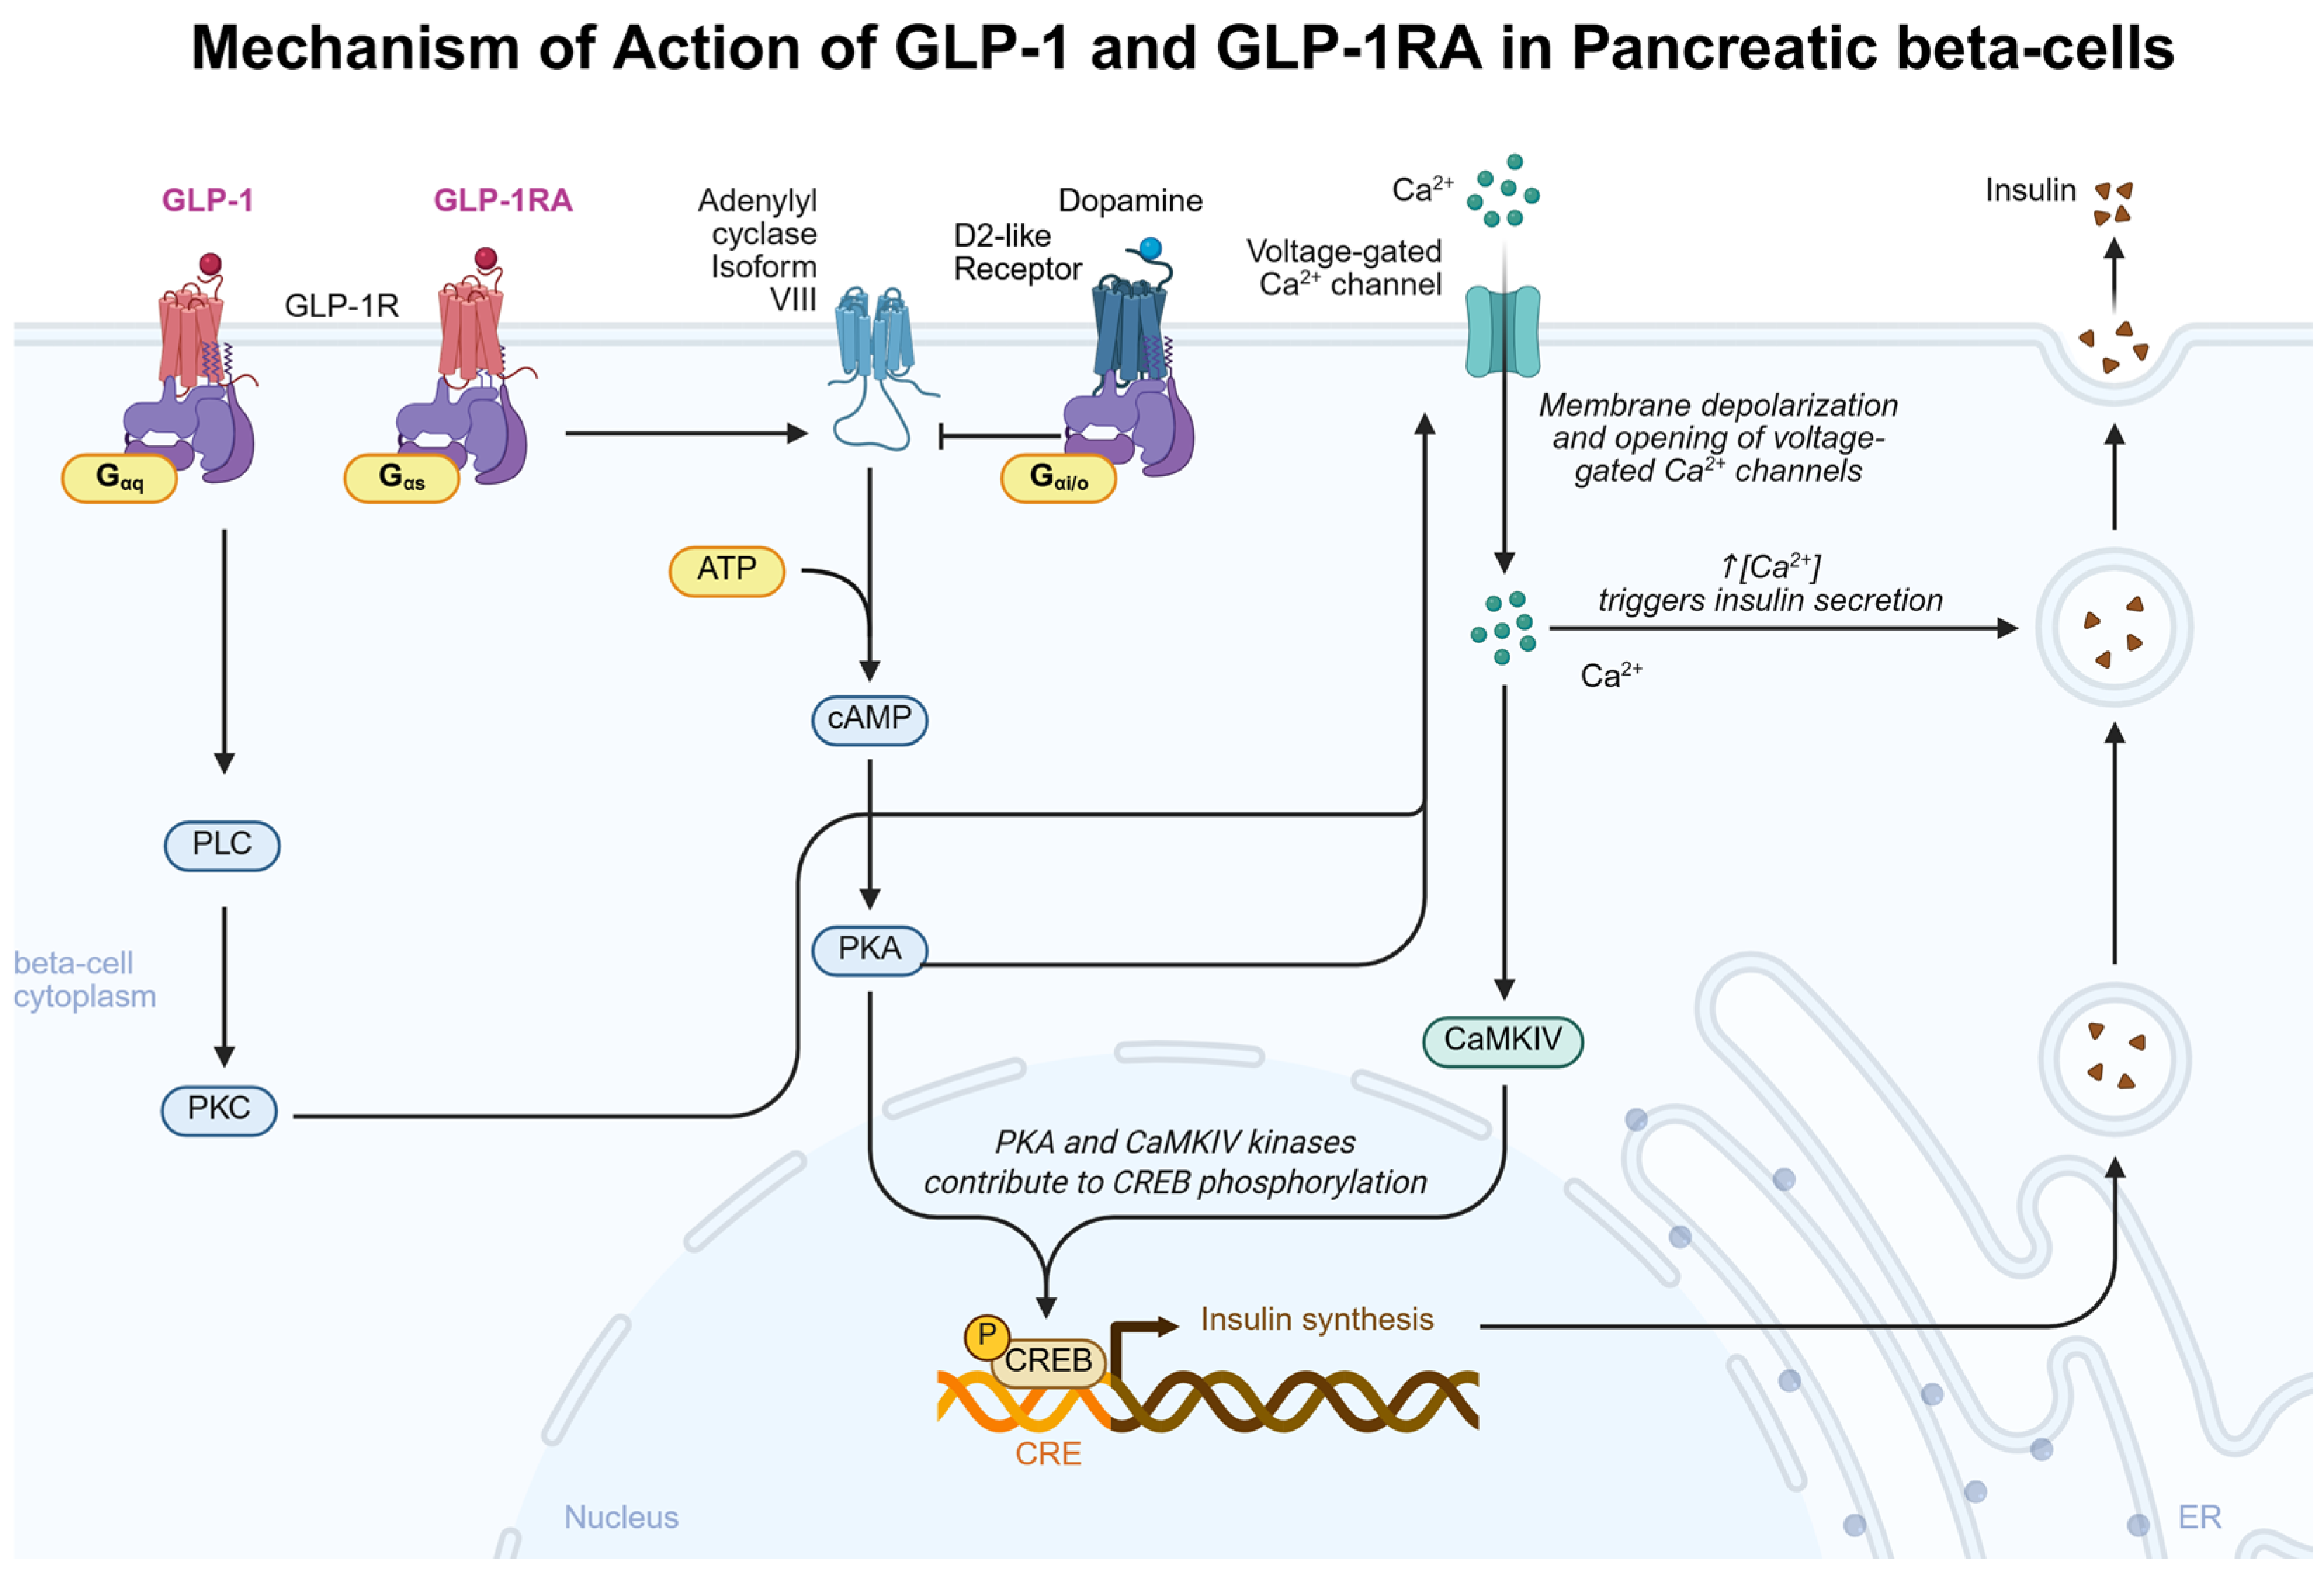
At its core, an agonist is a molecule that binds to a receptor and activates it, much like a key turning a lock. For IIGLP‑1, the lock is the IIGLP‑1 receptor (IIGLP‑1R), a G‑protein‑coupled receptor found on pancreatic beta cells, neurons in the brain, and adipose tissue.
When an IIGLP‑1 agonist attaches to IIGLP‑1R, several downstream events unfold:
- Enhanced insulin secretion: The receptor’s activation triggers a cascade involving cyclic AMP (cAMP), ultimately prompting beta cells to release more insulin in a glucose‑dependent manner. This means the drug amplifies insulin only when blood sugar is high, reducing hypoglycemia risk.
- Reduced glucagon release: Glucagon, the hormone that raises blood glucose, is suppressed, creating a more balanced glucose environment.
- Appetite suppression: Signals travel to the hypothalamus, the brain’s hunger center, where they dampen the urge to eat. This effect appears slower than GLP‑1’s but may be additive.
- Improved lipid handling: In adipose tissue, IIGLP‑1 signaling encourages fatty‑acid oxidation and modestly reduces lipogenesis, which could translate into lower liver fat over time.
Importantly, because the agonist’s action is tied to existing physiological pathways, it tends to preserve the body’s natural feedback loops—an advantage over some synthetic insulin secretagogues that act indiscriminately.
Clinical Development: Where Are We Now?
Several biotech firms have advanced IIGLP‑1 agonists into early‑phase trials. While full trial data remain limited, the emerging picture is cautiously optimistic:
- Phase 1 safety: Small groups of healthy volunteers tolerated single‑dose administrations with mild gastrointestinal side effects—similar to those seen with GLP‑1 drugs.
- Phase 2 efficacy signals: In a modest study of adults with type 2 diabetes, participants receiving the agonist showed an average HbA1c reduction of 0.5–0.7% after 12 weeks, alongside a 2–3% body‑weight loss.
- Combination potential: Ongoing trials are testing the agonist alongside a GLP‑1 analogue, aiming to capture synergistic effects without a proportional increase in side effects.
Regulatory agencies have not yet issued formal guidance, but the pathway mirrors that of other incretin‑based therapies, suggesting a relatively clear road to approval if larger studies confirm these early trends.
Potential Benefits and Risks
Every new therapeutic class carries a balance of promise and uncertainty. Here’s a quick rundown of what clinicians and patients might expect:
Benefits
- Glucose‑dependent insulin boost reduces the danger of low blood sugar episodes.
- Weight‑loss support may be especially valuable for patients who struggle with diet alone.
- Complementary action could allow lower doses of existing GLP‑1 drugs, potentially easing tolerability issues.
Risks
- Gastrointestinal discomfort (nausea, mild diarrhea) remains the most common side effect.
- Uncertain long‑term effects on pancreatic health, a topic still under investigation for other incretin agents.
- Potential drug interactions with other glucose‑lowering medications, requiring careful dose titration.
Physicians will need to weigh these factors against individual patient profiles, just as they do with any diabetes or obesity medication.
Frequently Asked Questions
What differentiates an IIGLP-1 agonist from a GLP‑1 drug?
While both target incretin pathways, IIGLP‑1 agonists primarily enhance insulin secretion and satiety through a separate receptor. This can provide additive glucose control and weight loss when used alongside GLP‑1 agents.
Can I use an IIGLP-1 agonist if I already take insulin?
In theory, yes, but dosage adjustments are essential. Because the agonist raises insulin only when glucose is high, it may lower the required basal insulin dose, reducing the risk of hypoglycemia.
How soon might these drugs be available?
Given that most candidates are still in Phase 2, a realistic timeline points to market entry in the next 4–6 years, assuming trial results remain favorable and regulatory review proceeds without major hurdles.
Are there lifestyle changes that enhance the drug’s effect?
Adopting a balanced diet and regular physical activity can amplify the metabolic benefits of any incretin therapy, including IIGLP‑1 agonists. Even modest weight loss can improve insulin sensitivity, making the drug’s action more efficient.